
Medical detox is the medically supervised management of withdrawal, not treatment for addiction itself. It has three jobs, defined in SAMHSA guidance: evaluate, stabilize, and get the person into ongoing treatment. Withdrawal from alcohol and benzodiazepines can be fatal; withdrawal from opioids is rarely fatal in a healthy adult but carries a serious post-detox overdose risk because tolerance drops fast. The decisive variable is the ASAM withdrawal-management level: 3.2-WM has no 24-hour nursing, 3.7-WM does, and 4-WM is hospital-level care with immediate access to acute medicine. A beautiful residence operating at 3.2-WM is not a higher level of care than a plain hospital unit at 4-WM. It is a lower one.
- Detox is stabilization, not treatment: SAMHSA is explicit that withdrawal management alone does little for long-term outcomes without a step-down into ongoing care.
- Alcohol and benzodiazepine withdrawal can be life-threatening; opioid withdrawal usually is not, but the post-detox overdose risk from lost tolerance is the danger people underestimate.
- The label that matters is the ASAM level (3.2-WM / 3.7-WM / 4-WM): it tells you the staffing and monitoring behind the door. Décor tells you nothing about it.
- Severity is scored, not guessed: CIWA-Ar for alcohol and COWS for opioids drive medication decisions hour by hour.
- Insurers authorize detox in short increments with concurrent review, which is why the plan for day four should exist before day one.
typical duration of medically supervised withdrawal from alcohol or opioids
Source: Clinical guidance
ASAM care levels of withdrawal management, from ambulatory (1-WM) to hospital (4-WM)
Source: ASAM Criteria
window in which delirium tremens typically appears — a medical emergency
Source: Clinical guidance
insurance coverage for withdrawal management is protected under federal law
Source: U.S. DOL
What medical detox is — and what it is not
Medical detox, properly called withdrawal management, is the supervised process of allowing a substance to leave the body while the physical and psychological consequences are managed clinically. SAMHSA frames it as three distinct jobs: evaluation (what is in the system, what else is going on medically and psychiatrically), stabilization (getting the person through withdrawal safely and humanely), and fostering entry into treatment (making sure the person walks into ongoing care rather than out of the front door).
That third job is the one the industry quietly skips. Detox is highly marketable: it is short, dramatic, and easy to sell as a fresh start. But withdrawal management on its own addresses the physical dependence and leaves the disorder untouched. The person who completes a beautiful seven-day detox and goes home with a phone number has been stabilized, not treated.

The three residential levels of withdrawal management
This is the single most useful thing to understand before choosing anywhere. The American Society of Addiction Medicine defines withdrawal management by clinical capability, not by comfort. Two facilities can look identical in photographs and sit two levels apart in what they can actually do if something goes wrong at 3 a.m.
ASAM describes five withdrawal-management levels in total. Two are ambulatory, 1-WM without extended on-site monitoring and 2-WM with it, and suit mild, low-risk withdrawal managed while living at home. The three below are the ones that involve staying somewhere, and they are where the decision usually sits.
ASAM withdrawal-management levels, plainly stated
| Level | What is actually on site | Typically appropriate for | What it cannot do |
|---|---|---|---|
| 3.2-WM | Clinically managed residential; staff present, but no 24-hour nursing or on-site physician | Mild to moderate withdrawal, medically stable, no seizure history | Manage a seizure, DTs, or an acute medical emergency on site |
| 3.7-WM | 24-hour nursing, physician availability, medically monitored protocols | Moderate to severe withdrawal, complicating conditions, prior severe withdrawal | Provide full hospital-level intensive care |
| 4-WM | Hospital setting: 24-hour medical and nursing care, immediate acute-care access | Severe withdrawal, unstable medical or psychiatric comorbidity, high seizure or DT risk | Provide the residential, restorative environment of a longer stay |
Levels are matched to withdrawal risk and medical complexity. A higher price does not raise a facility from 3.2-WM to 3.7-WM; only staffing and clinical capability do.

Which substances make withdrawal medically dangerous
Withdrawal risk is not uniform. The two categories that can kill are frequently the two people assume are gentler, because they are legal or prescribed.
Alcohol
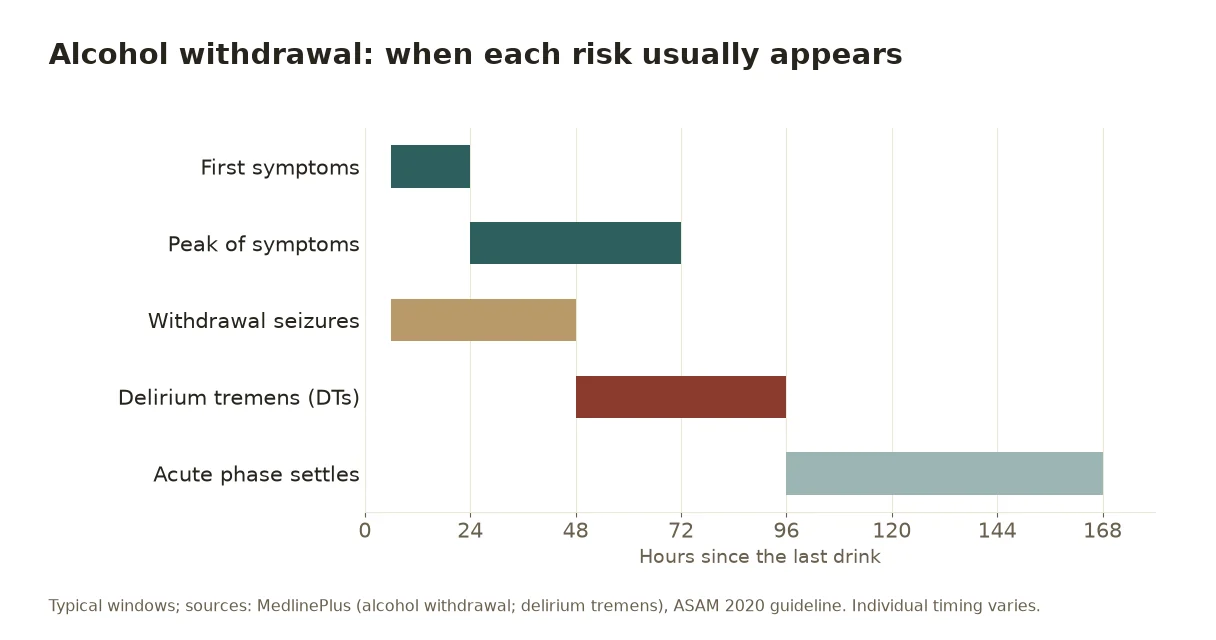
Can be fatalSymptoms typically begin 6–24 hours after the last drink. Seizures cluster in the first 48 hours; delirium tremens (confusion, agitation, autonomic instability) typically appears at 48–96 hours and is a medical emergency requiring immediate care. A history of prior withdrawal seizures or DTs raises risk sharply.
Benzodiazepines
Can be fatalThe most under-respected withdrawal in addiction medicine. Abrupt discontinuation can cause seizures, and symptoms may persist for weeks or months rather than days. Management is a structured taper, not a rapid detox, which is why a seven-day program is often the wrong shape for a long-term benzodiazepine dependence.
Opioids
Rarely fatal, high risk afterAcute withdrawal is intensely unpleasant (pain, vomiting, diarrhea, insomnia) but is not usually life-threatening in an otherwise healthy adult. The lethal danger comes afterwards: tolerance falls fast during abstinence, and a return to a previously ordinary dose can cause fatal overdose. This is why medication for opioid use disorder matters more than the detox itself.
Stimulants
Psychiatric riskCocaine and methamphetamine withdrawal is primarily psychological: profound fatigue, hypersomnia, anhedonia, and depression that can include suicidal thinking. There is no FDA-approved medication for stimulant withdrawal, so the clinical work is monitoring, psychiatric safety, and sleep.

Alcohol withdrawal symptoms: from mild to medical emergency
Alcohol withdrawal happens because the brain adapts to steady drinking. When the alcohol stops, the nervous system is left overexcited. Symptoms range from uncomfortable to life-threatening, and the early ones do not predict which way it will go.
- Mild: anxiety, shaky hands, sweating, nausea, headache, poor sleep and a fast heartbeat.
- Moderate: a stronger tremor, vomiting, high blood pressure, fever, irritability and confusion.
- Hallucinations: seeing, hearing or feeling things that are not there, often with a clear mind, usually in the first two days.
- Withdrawal seizures: most often 6 to 48 hours after the last drink.
- Delirium tremens (DTs): severe confusion, agitation, fever, drenching sweats and an unstable pulse and blood pressure, usually 48 to 96 hours after the last drink. The DTs are a medical emergency.
Call 911 for a seizure, confusion, hallucinations with fever, chest pain, or vomiting that will not stop. A same-day medical assessment is wise for anyone with a past seizure or DTs, weeks of heavy daily drinking, regular use of sedatives such as benzodiazepines, or serious heart, liver or lung disease.
Alcohol withdrawal timeline: how long it lasts
How long does alcohol withdrawal last? For most people the acute phase is over within five to seven days. The timing below is typical, not a promise: older adults, people with liver disease and people who also used sedatives can run later and longer.
Alcohol withdrawal, hour by hour
| Time since last drink | What typically happens | What to watch for |
|---|---|---|
| 6–12 hours | Tremor, anxiety, sweating, nausea, poor sleep | Symptoms can start while alcohol is still in the blood |
| 12–48 hours | Symptoms peak for many people; hallucinations possible | Withdrawal seizures cluster in this window |
| 48–96 hours | Mild cases usually improve; the DTs can begin | Confusion, fever and a racing heart need emergency care |
| 4–7 days | Acute withdrawal usually resolves | Sleep and mood are still disrupted |
| Weeks to months | Poor sleep, low mood, anxiety, craving | Relapse risk; time to start relapse-prevention medication |
Medication given during detox changes this curve. Untreated, the 48 to 96 hour window is the most dangerous.
How clinicians actually measure severity
Good withdrawal management is not improvization. Two validated instruments drive most decisions, and it is entirely reasonable to ask a program whether it uses them.
CIWA-Ar (Clinical Institute Withdrawal Assessment for Alcohol, revised) scores ten domains: tremor, sweats, anxiety, agitation, nausea, headache, orientation, and three categories of disturbance. Scores are taken repeatedly, and medication is given symptom-triggered against the score rather than on a fixed schedule. This approach generally reduces total medication used and shortens treatment compared with rigid dosing.
COWS (Clinical Opiate Withdrawal Scale) scores eleven domains for opioid withdrawal and, critically, determines when buprenorphine can be started. Give it too early and it displaces the opioid still on the receptor, precipitating a far worse withdrawal. A program that starts buprenorphine by the clock rather than by the score is doing it wrong.

Medications used in withdrawal management
Medications in detox do two different jobs: they carry a person through acute withdrawal, and, separately, they treat the underlying disorder afterwards. Conflating the two is a common and costly error.
Benzodiazepines (alcohol withdrawal)
Acute phaseFirst-line for alcohol withdrawal, dosed against CIWA-Ar scores. They suppress the nervous-system hyperactivity that drives seizures and delirium. Used for days, then tapered off: they are a bridge, not a destination.
Buprenorphine
FDA-approved for OUDA partial opioid agonist that both eases withdrawal and can continue as long-term treatment for opioid use disorder. Timing of the first dose is governed by COWS score to avoid precipitated withdrawal.
Methadone
FDA-approved for OUDA full agonist dispensed through licensed opioid treatment programs. Strong evidence for retention in treatment; the structure it requires is a burden for some patients and a scaffold for others.
Naltrexone
FDA-approved for AUD & OUDAn opioid antagonist available as a daily tablet or a monthly injection. It requires a fully detoxed patient before starting, which is exactly why it belongs in the conversation during detox rather than after it.
Acamprosate & disulfiram
FDA-approved for AUDAcamprosate supports abstinence after alcohol withdrawal resolves; disulfiram creates an aversive reaction to alcohol and suits a specific, motivated subset of patients. Neither manages acute withdrawal.

Medications for alcohol withdrawal: benzodiazepines, phenobarbital and the rest
Benzodiazepines are the first-line medication for alcohol withdrawal in the ASAM 2020 guideline. They treat symptoms and are the class with the best evidence for preventing withdrawal seizures and delirium. Chlordiazepoxide (Librium) and diazepam are long-acting choices; lorazepam is often preferred when the liver is impaired. Doses are usually triggered by a symptom score such as the CIWA-Ar rather than given on a fixed schedule.
Phenobarbital is an alternative used in hospitals when benzodiazepines are unsuitable or not working, and only where staff can monitor breathing closely. Carbamazepine or gabapentin may be used for mild withdrawal in outpatient care. Thiamine (vitamin B1) is given to protect against Wernicke encephalopathy, a brain injury linked to heavy drinking. None of these replaces the decision about where detox should happen, which the levels above set out. After detox, relapse-prevention medication is covered on our medication-assisted treatment page, and longer care on alcohol rehab.
The first seventy-two hours
The shape of a detox is predictable enough to plan around. For alcohol, the first six to twenty-four hours bring tremor, anxiety, sweating and rising pulse. The window from twelve to forty-eight hours carries the highest seizure risk. Delirium tremens, when it occurs, typically emerges between forty-eight and ninety-six hours, which is precisely why a program without 24-hour nursing is making a bet on the third night.
Opioid withdrawal follows the half-life of the drug: short-acting opioids produce symptoms within roughly eight to twelve hours, peaking around day two and easing over three to five days, while methadone withdrawal starts later and lasts substantially longer. Benzodiazepine withdrawal refuses to fit this frame at all: a proper taper is measured in weeks and months, and any program promising to "detox" a long-standing benzodiazepine dependence in a week should be questioned closely.

Can I just detox at home, quietly?
Sometimes, and sometimes that decision is fatal. Opioid withdrawal at home is miserable but rarely dangerous for a healthy adult. Alcohol and benzodiazepine withdrawal are different: seizures and delirium tremens are genuine medical emergencies, and the people most likely to attempt a private home detox are often the ones with the longest, heaviest histories, which is precisely the risk profile that needs monitoring. The honest answer requires someone to take a history first. That call costs nothing.
Will detox mean my life stops for a month?
Detox itself is usually days, not weeks: commonly three to ten. What follows is the real time commitment, and it is negotiable in a way people assume it is not: partial hospitalization and intensive outpatient exist precisely so that stabilization does not have to mean disappearing. The mistake is treating detox as the whole plan and then having no plan on the day it ends.
Is an expensive detox actually safer?
Not automatically, and this is the most important thing on this page. Price buys privacy, space, food, and staff-to-patient ratio. It does not buy an ASAM level. Ask directly: is this 3.2-WM, 3.7-WM, or 4-WM, is there 24-hour nursing on site, and what is the escalation route to a hospital? A residence that answers those three questions clearly is telling you more than any photograph.
What luxury actually buys — and what it cannot
It would be dishonest for a site like this one to pretend that comfort is irrelevant. It is not. Privacy protects careers and families. Space, food, sleep, and a low staff-to-patient ratio make a physiologically brutal week more bearable, and people who are less miserable are measurably more likely to stay through to the step-down that actually changes outcomes. Discretion has real value when the alternative is a person refusing care altogether because they cannot risk being recognized.
But there is a hard line, and it deserves stating plainly: money does not buy clinical capability. It does not create 24-hour nursing where there is none. It does not put a physician on site. It does not shorten the seizure window or make delirium tremens less dangerous. When a private residence and a hospital unit disagree on level of care, the hospital is not the downgrade: it is often the correct answer, and a program willing to tell you so is one worth trusting.
The day-four problem
Here is the pattern that quietly ruins the most expensive detoxes. Detox is the easiest level of care to get authorized and the easiest to complete: it is short, it has a clear endpoint, and it produces an immediate, genuine feeling of improvement. On day four, the physical crisis has passed. The person feels better than they have in months. Every incentive, internal and external, points towards going home.
And the disorder is entirely intact. Physical dependence has been unwound; the conditioning, the psychiatric comorbidity, the relationships, and the environment that produced the pattern are all untouched. For opioids specifically, this is also the moment of maximum overdose danger, because tolerance has dropped while the habit of a previous dose has not. The clinical literature is consistent on this point: withdrawal management without a step-down into ongoing treatment is not a course of treatment. It is a pause.

Questions to ask before you admit
These six questions separate programs quickly, and none of them require clinical training to ask.
What ASAM withdrawal-management level are you?
The answer should be immediate and specific: 3.2-WM, 3.7-WM, or 4-WM. Hesitation or marketing language in place of a level is itself the answer.
Is there 24-hour nursing physically on site?
"On call" is not the same as on site. For anyone with meaningful alcohol or benzodiazepine withdrawal risk, this distinction is the whole conversation.
What is your escalation route to a hospital?
A competent program has a named receiving facility, a transfer protocol, and a realistic transport time. Ask for all three.
Do you use CIWA-Ar or COWS scoring?
Symptom-triggered dosing against a validated score is the standard of care. Fixed-schedule medication regardless of presentation is a step behind it.
Who prescribes medication for the disorder itself?
If nobody at the program can start buprenorphine, naltrexone, or acamprosate, the most evidence-backed part of treatment is being left to someone you have not met yet.
What exactly happens on the day detox ends?
The correct answer names a level of care, a start date, and a person. "We will discuss discharge planning" is not a plan.
Choosing between hospital and residential detox
For most people the honest choice is between 3.7-WM in a residential setting and 4-WM in a hospital, and it turns on medical complexity rather than preference. A history of withdrawal seizures or delirium tremens, significant cardiac or hepatic disease, pregnancy, unstable psychiatric illness, or a high-dose benzodiazepine dependence all push towards hospital-level care. Uncomplicated moderate withdrawal in a medically stable person is well within the capability of a good 3.7-WM residence.
Two practical notes. First, the two settings are not rivals: a common and sensible sequence is a short 4-WM admission to get through the dangerous window, followed by transfer into a residential program for the actual treatment. Second, polysubstance use changes the maths: someone withdrawing from both alcohol and benzodiazepines is not in two mild withdrawals but in one complicated one, and should be assessed accordingly.

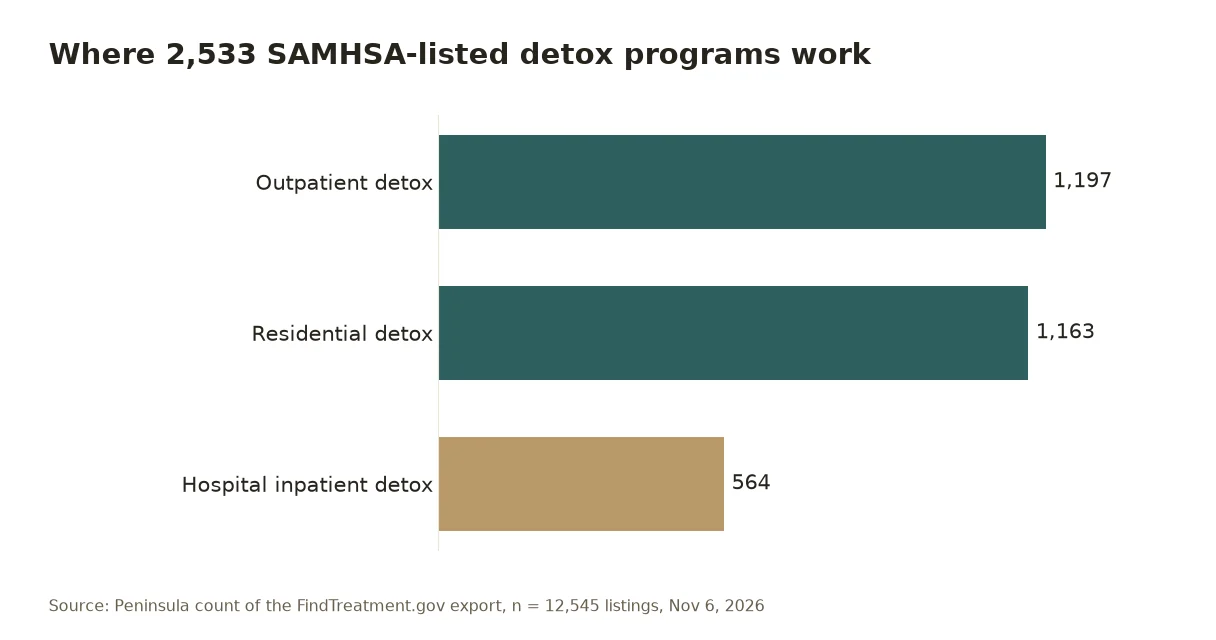
Where detox actually happens: our count of 2,533 SAMHSA-listed programs
We counted the federal FindTreatment.gov list of substance use treatment facilities for listings that offer detoxification, and where they do it.
| What the listing reports | Count | Share |
|---|---|---|
| Listings offering detoxification | 2,533 of 12,545 | 20.2% |
| Hospital inpatient detox | 564 | 4.5% |
| Residential detox | 1,163 | 9.3% |
| Outpatient detox | 1,197 | 9.5% |
| Detox programs treating alcohol withdrawal | 2,027 of 2,533 | 80.0% |
| Detox programs treating benzodiazepine withdrawal | 1,886 of 2,533 | 74.5% |
| Detox programs routinely using medication | 2,336 of 2,533 | 92.2% |
| Detox programs listing acamprosate for afterward | 1,459 of 2,533 | 57.6% |
Source: Peninsula count of the FindTreatment.gov facility export (substance use, all U.S. listings, downloaded November 6, 2026; n = 12,545 listings). Facilities self-report their services to SAMHSA; a facility can list several settings, and some organizations appear once per site.
Only about one listing in five offers detox at all, and just 564 do it in a hospital, the setting for complicated alcohol withdrawal. When a program advertises "detox", ask which of these three settings it means.
What comes after: the step-down that decides the outcome
The measure of a detox is not how comfortable it was. It is whether the person was still in treatment ninety days later. That makes the step-down plan the most consequential thing decided during the stay, and it should be settled early rather than in a discharge meeting on the final morning.
The realistic paths are a residential program for people whose home environment is itself part of the problem, partial hospitalization for those who need clinical intensity but can sleep at home, and intensive outpatient for people stepping down or unable to leave work and family entirely. Alongside any of them, medication for opioid or alcohol use disorder should be an explicit decision rather than an omission, and for opioid use disorder in particular, starting that medication during detox rather than after it is one of the few choices on this page with a clear evidence base behind it.

This is general information, not medical advice
Clinical protocols, durations, and costs vary by individual history and by programme. Figures on this page are typical ranges and illustrative examples, not medical advice and not a quote. Withdrawal from some substances can be dangerous; decisions about level of care belong with a qualified clinician who has examined you. For free, confidential help finding treatment, call SAMHSA 1-800-662-HELP.
Medical Detox coverage, answered
How long does medical detox take?
Can withdrawal actually kill you?
What is the difference between 3.7-WM and 4-WM?
Is detox alone enough to treat addiction?
Why is overdose risk higher after detox?
Can I detox at home?
What is CIWA-Ar?
When can buprenorphine be started?
Does insurance cover medical detox?
Does a more expensive detox mean a safer one?
What happens if I need to detox from more than one substance?
What should be arranged before detox begins?
What are the first signs of alcohol withdrawal?
How long does alcohol withdrawal last?
When is alcohol withdrawal an emergency?
What medication is used for alcohol withdrawal?
Explore the full continuum of care
Sources & references
- SAMHSA — TIP 45: Detoxification and Substance Abuse Treatment
- SAMHSA — National Helpline and treatment locator
- American Society of Addiction Medicine — The ASAM Criteria
- NIDA — Treatment and Recovery
- NIAAA — Alcohol Use Disorder: Treatment
- SAMHSA TIP 63 — Medications for Opioid Use Disorder (updated 2021)
- CDC — Preventing opioid overdose
- MedlinePlus — Alcohol withdrawal
- U.S. Department of Labor — Mental Health and Substance Use Disorder Parity
Reviewed November 6, 2026 · Peninsula editorial standards. Medical Detox-specific facts cite Medical Detox plan documentation; regulatory facts cite U.S. federal sources.
Know your Medical Detox numbers first.
A twenty-five-minute call establishes your out-of-network residential benefit, deductible status, and whether a single-case agreement is worth pursuing: a written best, middle, and worst-case cost scenario for your specific plan.